
Five years ago, most people had never heard of a GLP-1 receptor agonist. Today, semaglutide (Ozempic, Wegovy) and tirzepatide (Mounjaro, Zepbound) are household names, and they've permanently reshaped how clinicians think about obesity — not as a failure of willpower, but as a treatable metabolic condition. But the research pipeline didn't stop there. The next chapter in incretin science is already being written in Phase 3 trial data, and it centers on a class of molecules researchers call
Join our telegram channel for instant updates 🎖️
"triple agonists."
From One Receptor to Three
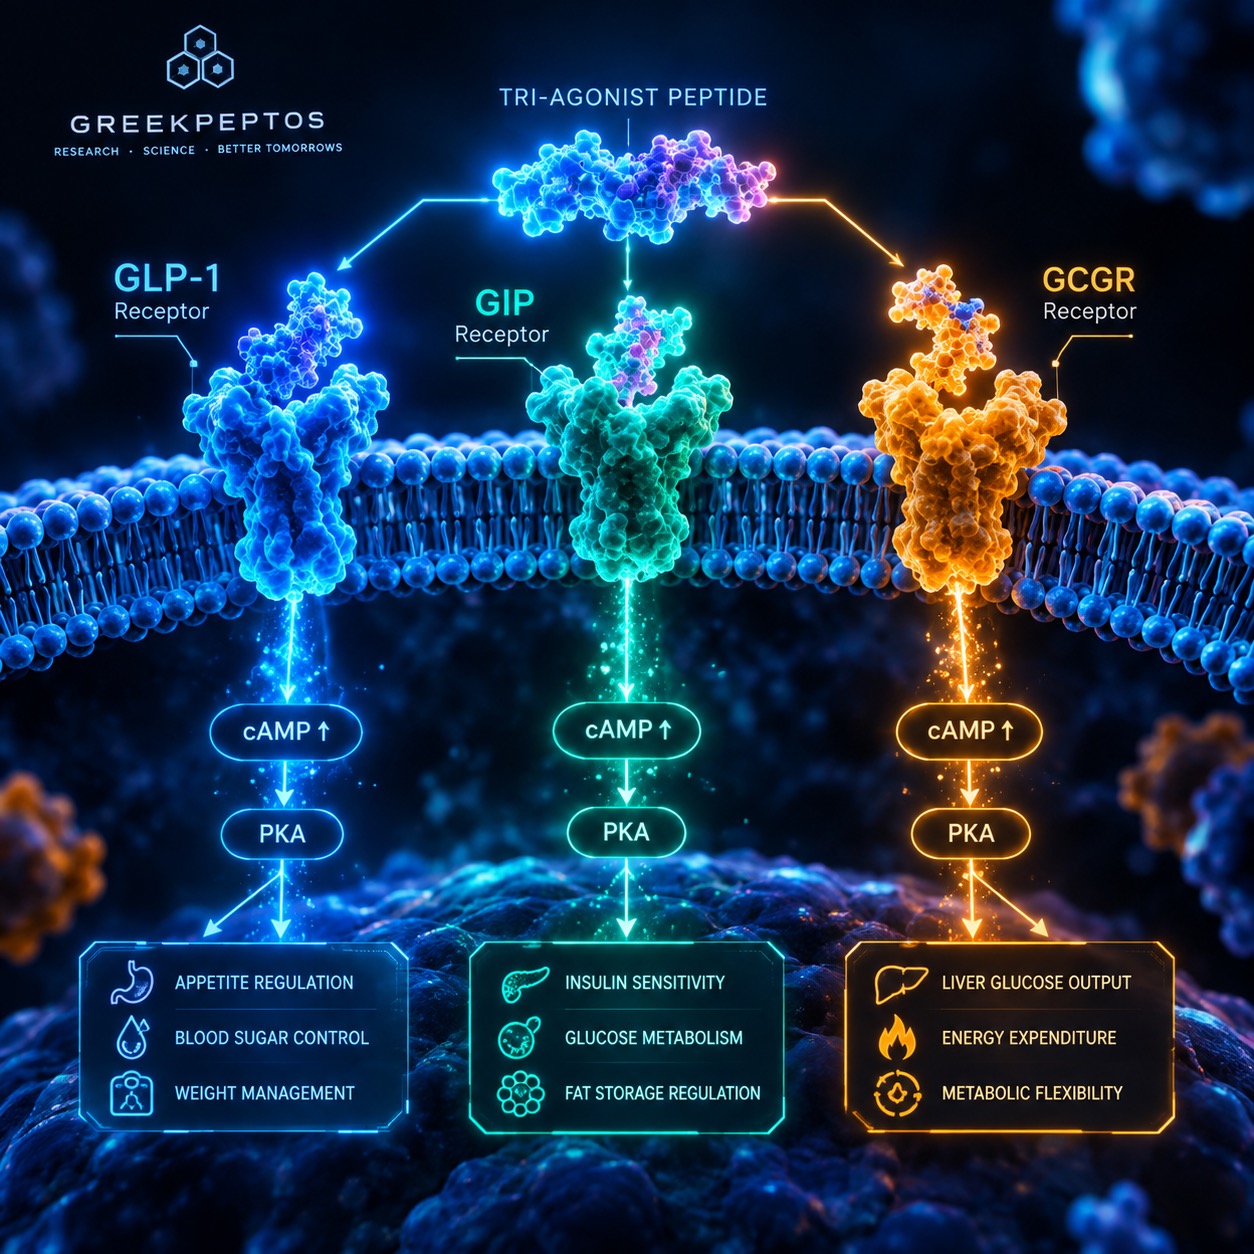
The logic behind this progression is straightforward. Semaglutide activates a single receptor — GLP-1. Tirzepatide was the first to combine two: GLP-1 and GIP, an incretin hormone that also helps regulate insulin secretion. The newest candidate, retatrutide (Eli Lilly's LY3437943), goes a step further by activating a third receptor: glucagon.
That third target matters mechanistically. While GLP-1 and GIP work to suppress appetite, the addition of glucagon signaling is thought to increase energy expenditure and fat breakdown, rather than acting on appetite alone. It's a different lever on the same underlying system, and it's the reason retatrutide has generated so much attention in the metabolic research community. oregonstate
What the Trial Data Actually Shows
It's worth being precise here, because the numbers are genuinely striking. In the Phase 3 TRIUMPH-1 trial, 2,339 adults without diabetes were randomized to retatrutide at 4mg, 9mg, or 12mg doses, or placebo, over 80 weeks. At 80 weeks, participants on the 12mg dose lost an average of 28.3% of body weight — roughly 70 pounds — compared with 2.2% in the placebo group, and nearly half of participants on that dose achieved at least 30% weight loss. An extension study in participants with higher baseline BMI found continued reduction through 104 weeks, with mean weight loss reaching 30.3% in that group. epocrates logo +2
In a separate Phase 3 trial focused on people with type 2 diabetes, the 40-week study found the 12mg dose produced a mean 15.3% reduction in bodyweight alongside a 1.94% reduction in HbA1c, compared to smaller changes in the placebo arm. Earlier Phase 2 data, published in the New England Journal of Medicine, found that participants on the highest tested dose achieved 24.2% mean weight loss over 48 weeks, versus 2.1% for placebo — at the time, one of the largest effect sizes reported for any drug in this class. thelimbicsuperpower
Beyond the scale, researchers are watching cardiometabolic markers closely. Trial data have shown meaningful reductions in systolic blood pressure — up to 14 mmHg in some analyses — along with improvements in non-HDL cholesterol and triglycerides, suggesting the benefits of triple agonism may extend well past body weight alone. oregonstate
It's important to note that no completed head-to-head randomized trial has directly compared retatrutide to tirzepatide or semaglutide. The apparent advantage over dual agonists comes from indirect comparisons across separate trials, not a single controlled study — a distinction that matters for anyone evaluating the hype critically. superpower
Where Things Actually Stand, Regulatorily
Here's the part that responsible reporting on this topic can't skip: retatrutide is not an approved medication. Eli Lilly is developing it as a treatment for obesity and weight-related medical conditions, but as of the most recent regulatory updates, it remains an investigational compound in Phase 3 development, unavailable outside enrolled clinical trials, with no FDA-approved prescribing information in existence. Analysts anticipate an FDA submission sometime in late 2026 or 2027, but that timeline can shift, and approval is never guaranteed. Retatrutide FDA Approval Status +2
This is a genuinely exciting area of pharmaceutical research — but "investigational" is not the same as "available," and anyone encountering retatrutide, or any compound marketed under a similar name, outside a registered clinical trial should treat that as a red flag rather than an opportunity.
How to Evaluate Peptide Research Responsibly
If this space interests you — whether as a patient, a student, or someone simply following the science — the most reliable move is to go straight to primary regulatory and research sources rather than relying on secondhand summaries (including this one):
- ClinicalTrials.gov (U.S. National Library of Medicine) — search "retatrutide" or "TRIUMPH" for the actual protocols, enrollment criteria, and posted results of ongoing trials.
- FDA.gov — the definitive source for a drug's actual approval status, safety communications, and any warnings issued about unapproved compounded or research-labeled versions.
- NIH / NIDDK (National Institute of Diabetes and Digestive and Kidney Diseases) — for plain-language background on obesity pharmacology and incretin hormones.
- MHRA (UK Medicines and Healthcare products Regulatory Agency) — the UK equivalent of the FDA, useful for checking approval status and safety alerts in a UK context.
- NHS.uk — for balanced, non-commercial patient guidance on weight-management medications currently approved for use.
Peer-reviewed journals — NEJM, The Lancet, Nature Medicine — are where the actual trial data live, and abstracts are usually free to read even without full access.

The Bottom Line
The shift from single-target to triple-target metabolic peptides represents one of the more consequential developments in obesity research in years, and the data from trials like TRIUMPH genuinely support the excitement. But excitement about a research pipeline is different from a compound being ready for real-world use. Until retatrutide — or anything like it — clears full regulatory review, the safest and most scientifically sound position is to follow the trial data as it publishes, and to get any actual treatment decisions from a licensed prescriber working from FDA- or MHRA-approved options.
